Ray Besharati, DDS, DMD, MS
A clicking jaw can sound concerning. But the sound alone does not tell us whether treatment is needed.
When clicking is painless, movement is comfortable and the jaw does not catch or lock, treatment directed at the noise is generally unnecessary. Pain, restricted movement or locking changes the question. The useful starting point is what the person is experiencing and how the jaw functions.
What does the click tell us?
One possible explanation is disc displacement with reduction. The small disc within the jaw joint changes its relationship to the moving joint surfaces, sometimes producing a click.
That is a possible mechanical explanation. It does not establish that the disc is causing pain, that damage is progressing, or that treatment must reposition it. Imaging findings also need to be interpreted alongside symptoms and function.
For clinicians, this distinction matters: identifying a finding and deciding whether to treat it are separate decisions.
Start with the complaint, then interpret the finding
A useful assessment asks:
- Is the click itself the concern, or is there pain?
- Does chewing, opening or clenching change the pain?
- Has the jaw caught or locked?
- Has opening, eating or another everyday activity become difficult?
- Is there a new bite change or relevant injury?
The examination should test the explanation suggested by the history.
The Diagnostic Criteria for Temporomandibular Disorders—DC/TMD—emphasize reproducing the patient’s familiar pain when assessing pain-related diagnoses. An incidental tender spot is different from reproducing the complaint that brought the patient in.
Even familiar pain is not a diagnosis by itself. The history and examination must also account for competing explanations, including dental, inflammatory and other conditions.
Would imaging change the decision?
An examination can support a working diagnosis, but clinical assessment has limitations when determining disc position.
The DC/TMD recommendations connect the need for a definitive disc diagnosis to whether the additional information would change treatment planning or prognosis. That is a more useful question than ordering a scan simply because a click is present.
When disc imaging is indicated, MRI evaluates the disc and other soft tissues. CBCT is useful for bony structures but does not directly show disc position. Choosing a scan begins with identifying the question it needs to answer.
What would treatment be trying to accomplish?
Before recommending an intervention, define its purpose.
Are we addressing pain? Difficulty eating? Repeated locking? A separate need to protect teeth? These are different indications.
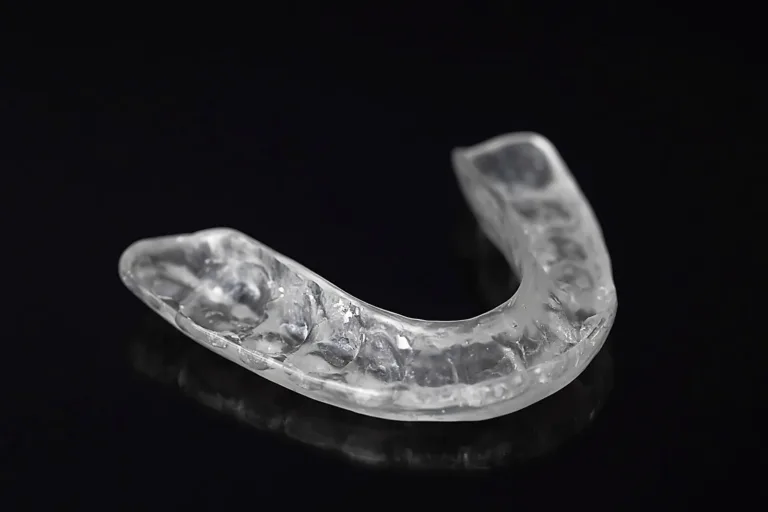
An appliance is not an automatic next step because a joint clicks. NIDCR’s treatment guidance places simpler approaches first and cautions against irreversible procedures. Crowns, tooth grinding or orthodontic treatment should not be proposed merely to eliminate a joint noise.
Useful questions before starting treatment include:
- What problem are we treating?
- What supports the proposed diagnosis?
- What would make us reconsider the plan?
- How will we assess whether the treatment remains appropriate?
When should clicking be reassessed?
Arrange an assessment when clicking accompanies pain, catching, locking, reduced movement or a change in how the teeth meet. Painless functional difficulty also deserves attention; the absence of pain does not make locking irrelevant.
For patients, these changes are more useful to report than the loudness of the click alone.
For clinicians, the central task is to connect the history, examination and any necessary imaging to a defensible decision: observe, investigate, manage or refer.
Learn about a TMJ and orofacial pain evaluation or request an evaluation. Clinicians can use our professional referral page.
This article provides general education. Individual recommendations require an appropriate clinical assessment.